Trabeculectomy is recommended when glaucoma continues to threaten useful vision and the pressure target cannot be reached safely with drops, laser treatment, or a less-invasive procedure. By the end, you will know which test results support surgery, when another treatment is more suitable, and what to ask before choosing a glaucoma surgeon in Chandigarh.
Key takeaways
- Trabeculectomy is considered when glaucoma damage threatens vision despite adequate treatment.
- One high eye-pressure reading alone does not justify trabeculectomy.
- Your target eye pressure depends on existing damage and future-loss risk.
- Regular pressure checks and wound management are essential after surgery.
When does glaucoma justify trabeculectomy?
Trabeculectomy is justified when glaucoma threatens useful vision and the target intraocular pressure (IOP) cannot be reached safely with correctly used drops, laser treatment, or less-invasive surgery. A single high reading is not enough; the recommendation rests on the damage, pressure pattern, and risk of further loss.
An ophthalmologist may recommend trabeculectomy eye surgery when:
- IOP remains above target despite prescribed drops used correctly.
- Tests document worsening of the optic nerve or visual field.
- Medication causes side effects or cannot be tolerated.
- The treatment burden makes adherence unreliable.
- Advanced damage requires a very low target pressure to protect remaining vision.
Glaucoma stage alone does not decide the operation. The ophthalmologist also weighs the rate of progression, life expectancy, visual demands, the condition of the other eye, and the pressure needed to preserve useful sight. Rapid progression or serious risk to the better-seeing eye increases the urgency, but examination and reliable testing must confirm that risk.
Advanced glaucoma can require action even when you notice no symptoms. Peripheral field loss often goes unnoticed, while lost optic-nerve tissue cannot be restored. Trabeculectomy aims to lower pressure and prevent or slow further loss; it does not recover vision already lost.
Anyone considering trabeculectomy surgery in Chandigarh should ask what target IOP is required and whether progression is documented.
How does the surgeon decide whether surgery is appropriate?
A trabeculectomy recommendation rests on a pattern, not one high eye-pressure reading. The ophthalmologist repeats intraocular-pressure measurements, examines the optic nerve, and checks OCT scans of the retinal nerve fibre layer or ganglion-cell layer alongside visual-field tests.
Together, these show existing damage, whether it is progressing, and whether the results are reliable enough to justify surgery.
| Assessment | What it establishes | Why it matters |
|---|---|---|
| Repeated IOP readings | Pressure trend against target | Persistent elevation supports escalation |
| Optic-nerve examination and OCT | Structural damage or change | Confirms whether tissue is being lost |
| Visual-field testing | Functional vision loss and progression | Shows whether damage affects useful sight |
| Gonioscopy | Open angle or angle-closure mechanism | Determines whether another procedure comes first |
Gonioscopy can change the plan completely. Angle-closure glaucoma may need laser iridotomy or lens-based treatment before filtration surgery, while pseudoexfoliative, pigmentary, uveitic, neovascular, and childhood glaucoma follow different pathways. The surgeon also reviews previous drops, adherence, side effects, laser treatment, and any eye surgery.
Preparation includes a medical-history review, ocular-surface assessment, consent, and infection precautions. Do not stop warfarin, aspirin, or another medicine using a generic online schedule; obtain specific instructions from the treating doctor.
Take these questions to a consultation for glaucoma surgery in Chandigarh:
- What is my target pressure?
- Is progression documented?
- Are my visual-field and OCT results reliable?
- Is my better-seeing eye at risk?
- Why is trabeculectomy safer or more effective than the alternatives for me?
What does trabeculectomy do, and how does it differ from other treatments?
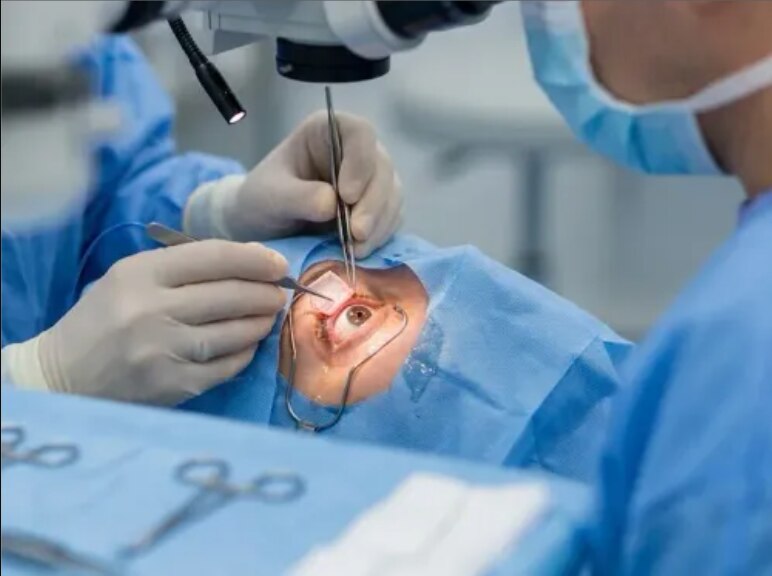
Trabeculectomy eye surgery creates a guarded drainage pathway for aqueous fluid. The surgeon makes an opening through the sclera, covers it with a scleral flap, and directs fluid from the front of the eye beneath the conjunctiva. The resulting filtering bleb releases fluid and lowers intraocular pressure.
Mitomycin C or 5-fluorouracil may be applied to limit scar formation. These medicines can improve drainage success but also increase the need for close monitoring because excessive filtration can cause very low pressure and related complications.
The procedure usually uses local anaesthesia, followed by an eye pad or shield. Your surgeon may combine it with cataract surgery when the lens, cataract symptoms, glaucoma severity, and target pressure support that plan. Staging the two operations is another option.
| Treatment | How it lowers pressure | Typical role |
|---|---|---|
| Eye drops | Reduce fluid production or increase outflow | First-line or ongoing treatment |
| Selective laser trabeculoplasty | Improves drainage through the natural angle | Often considered for suitable open-angle glaucoma |
| Minimally invasive glaucoma surgery | Adds a smaller internal drainage route | Earlier disease or a lower pressure target |
| Ahmed Glaucoma Valve | Diverts fluid through an implanted tube and plate | Selected complex or refractory glaucoma |
| Cyclophotocoagulation | Reduces fluid production by treating the ciliary body | Difficult cases or when other surgery is unsuitable |
| Trabeculectomy | Forms a subconjunctival filtering bleb | When very low pressure is needed |
Thus, glaucoma surgery in Chandigarh includes procedures with different risks and pressure-lowering strength. Trabeculectomy is more invasive but may achieve a lower pressure; less-invasive options can suit earlier disease or a different risk profile.
When is trabeculectomy not the preferred choice, and what follow-up does it require?
Trabeculectomy is not automatically the best operation. In angle-closure glaucoma, laser iridotomy, lens-based treatment, or another procedure may need to come first. Active inflammation or infection, severe conjunctival scarring, and a failed previous filtering operation can reduce success. A glaucoma drainage device may offer a safer or more reliable pathway.
The recommendation also depends on the glaucoma type:
- Pseudoexfoliative and pigmentary glaucoma may need disease-specific pressure control and laser or surgical planning.
- Uveitic glaucoma requires inflammation control before filtering surgery.
- Neovascular glaucoma often needs treatment of the new abnormal blood vessels and may favour a drainage device.
- Childhood glaucoma follows specialist paediatric pathways rather than an adult trabeculectomy plan.
The healing period is part of trabeculectomy surgery in chandigarh, not a single follow-up visit. Expect frequent pressure checks and possible steroid or antibiotic adjustments, suture adjustment or removal, bleb massage, or needling. Do not stop glaucoma or postoperative drops unless the operating ophthalmologist instructs you.
Low pressure, a shallow anterior chamber, choroidal effusion or haemorrhage, wound or bleb leak, infection, cataract progression, and scarring can occur. The bleb can scar and fail, leaving you needing drops, needling, revision, or another procedure.
Seek urgent ophthalmic assessment for pain, redness, discharge, or sudden vision reduction. A bleb infection can develop long after surgery.
How should you choose a glaucoma treatment hospital in Chandigarh?
Choose a glaucoma treatment hospital in Chandigarh that can support the entire healing period, not only the operation. Before booking trabeculectomy surgery in Chandigarh, identify the operating surgeon and ask how frequently they treat filtering-bleb complications.
| Check | What to ask | Why it matters |
|---|---|---|
| Operating surgeon | Who will perform my trabeculectomy, and who provides cover if they are unavailable? | You need clear responsibility for decisions after surgery. |
| Bleb experience | How often do you manage leaks, scarring, high or low pressure, and needling? | Bleb problems can require prompt treatment or revision. |
| Review schedule | When are pressure checks, suture adjustments, medication changes, and bleb assessments planned? | Early healing is part of the operation. |
| Urgent care | Who should I contact for pain, redness, discharge, or sudden vision reduction, including nights and weekends? | These symptoms can signal infection or another sight-threatening complication. |
| Glaucoma follow-up | Is a glaucoma subspecialist available for continuing reviews? | Long-term pressure control and progression monitoring remain necessary. |
Distance matters because healing can require several examinations and interventions over weeks or months. A nearby hospital reduces delays when the pressure changes or the bleb needs treatment.
Ask for a written explanation of your glaucoma type, current optic-nerve and visual-field findings, target pressure, previous treatments, why alternatives are less suitable, and the plan if the bleb scars.
Advanced Squint Centre is one centre where you can discuss these questions during specialist glaucoma assessment in Chandigarh; choose after examination, testing, and an individual risk-benefit discussion.
Related service
Glaucoma Surgery (Trabeculectomy) Glaucoma Surgery (Trabeculectomy) Advanced Squint Centre provides advanced Glaucoma Surgery (Trabeculectomy) in Chandigarh for patients with moderate to advanced glaucoma who require... View service → |
Frequently asked questions
When does glaucoma justify trabeculectomy?
Trabeculectomy is considered when glaucoma threatens useful vision and the target intraocular pressure cannot be reached safely with correctly used eye drops, laser treatment, or less-invasive surgery. A single high pressure reading is not enough; the decision also considers optic-nerve damage, visual-field loss, pressure patterns, and the risk of further loss.
How does a surgeon decide whether trabeculectomy is appropriate?
The assessment includes eye-pressure measurements, optic-nerve examination, optical coherence tomography, visual-field testing, medication use, previous laser or surgery, the type and severity of glaucoma, and your ability to attend follow-up. The surgeon balances the expected pressure reduction against risks such as scarring, infection, hypotony, and vision changes.
What does trabeculectomy do, and how does it differ from other treatments?
Trabeculectomy creates a controlled drainage pathway under the conjunctiva so aqueous fluid leaves the eye and lowers intraocular pressure. Unlike drops, it does not depend on daily dosing. Compared with laser or minimally invasive glaucoma surgery, it usually offers greater pressure reduction but requires more intensive healing care and carries more surgical risk.
When is trabeculectomy not the preferred choice?
It may not be preferred when glaucoma is mild, the target pressure is reached with drops or laser, the eye has a high scarring risk, the diagnosis or treatment plan is uncertain, or another procedure better suits the glaucoma type and the patient’s follow-up capacity. The choice depends on the individual examination rather than pressure alone.
What follow-up does trabeculectomy require?
Follow-up checks pressure, the surgical site, bleb function, inflammation, and vision. The surgeon may adjust steroid drops, release or revise sutures, or perform needling if scarring reduces drainage. Seek urgent review for severe pain, sudden vision loss, marked redness, discharge, or new flashes and floaters.
Keywords